
Hip Pain & Greater
Trochanter: PRP &
Regenerative Treatment
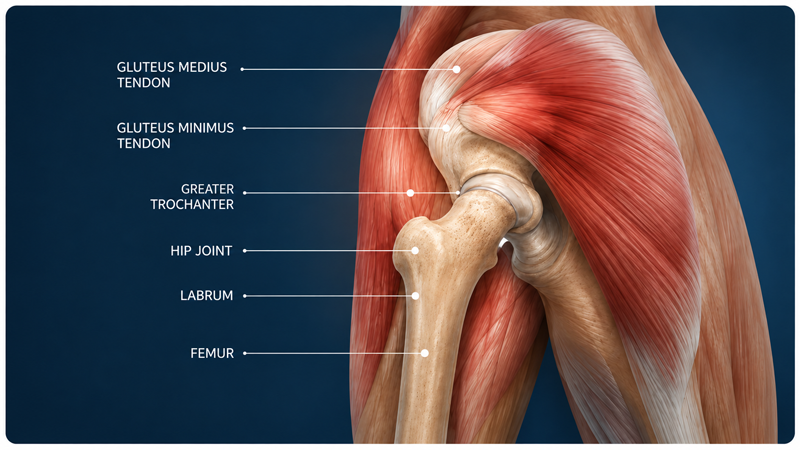
Hip pain is often treated as though it comes either from arthritis inside the joint or from “bursitis” on the outside. In reality, several structures may be contributing at the same time. The hip joint, labrum, capsule, supporting ligaments, and the gluteus medius and minimus tendons all help control load. Mapping which of those structures is actually painful matters before deciding what—or where—to inject.
PRP for Hip Pain
PRP uses a concentrated preparation made from your own blood to deliver platelets and healing signals to injured or degenerative tissue. Treatment may involve the hip joint, gluteal tendons, capsule, ligaments, labrum-related structures, or several targets depending on the findings.
Why Pain Mapping
Matters
An MRI may show several abnormalities, and not every finding is responsible for the pain. Pain Mapping combines examination, movement testing, ultrasound, imaging review, and diagnostic injections to identify which structures are actually contributing to your symptoms.
When PRP May Be Considered
- Gluteus medius or minimus tendinopathy and selected partial tears
- Greater trochanteric pain
- Mild-to-moderate hip arthritis
- Labral, capsular, or ligament problems
- Hip instability or incomplete healing
- Persistent pain after rehabilitation
- Exploring non-surgical options before surgery
Beyond PRP: Other Options
When damage is more significant, BMAC or adipose tissue scaffolding may be considered. Percutaneous tenotomy can also be useful for focal degenerative tendon problems. The choice depends on the tissues involved, stage of damage, and realistic healing capacity—not simply on selecting the most advanced treatment.
When Surgery May Be the Better Path
Recovery Is Part of the Treatment
Risks and Limitations
Temporary soreness, swelling, stiffness, or increased sensitivity is common. Results depend on the stage of joint disease, tendon quality, hip stability, overall health, and rehabilitation. PRP cannot reliably rebuild a severely damaged joint or reconnect a complete tendon tear. Bleeding, infection, or injury to nearby structures are uncommon but possible.
Frequently Asked Questions
No. Pain over the greater trochanter is commonly influenced by the gluteal tendons as well as the bursa. Ultrasound, examination, and diagnostic injections can help determine which structure is actually driving the pain.
PRP may be considered for selected gluteus medius or minimus tendinopathy and partial tears when the tendon still has a reasonable capacity to heal.
Yes, in selected degenerative gluteal tendon problems. Tenotomy addresses focal unhealthy tissue mechanically, while PRP may be used to support the healing response that follows.
No. The greater trochanter, gluteal tendons, SI region, and lumbar spine can produce overlapping symptoms. Pain Mapping helps separate them before treatment.
Looking for More Than Another Hip or Bursa Injection?
Find out whether the pain is coming from the joint, labrum, greater trochanter, gluteal tendons, instability—or a nearby structure mimicking the hip.